 Scribe
Examples
From the conversation to the signed document.
Two illustrative cases, start to finish: what was said in the room, and what ScribeIn wrote. Clinics, doctors and patients are fictional.
What is said in the room
Aaiye Rohan ji, baithiye. 46 saal, weight aaj 78 aaya hai na? Boliye, kya takleef hai?
Haan, 78. Doctor, teen din se bukhaar hai, thand lag ke aata hai. Kal raat 101.5 tak gaya tha.
Khaansi hai? Balgam aata hai?
Sookhi khaansi hai, balgam nahi. Poora badan dukh raha hai aur khaane ka bilkul mann nahi karta.
Pehle se koi bimari? Koi dawa chal rahi hai? Kisi dawa se allergy?
BP hai. 2022 se Telmisartan 40 roz subah leta hoon. Allergy kabhi nahi hui.
(examining) Temperature 100.8 hai, pulse 92, BP 138 by 86, oxygen 97. Gala laal hai, chest bilkul clear hai — infection neeche nahi gaya.
Viral fever hai, gale ke infection ke saath. Dolo 650 subah-dopahar-raat khaane ke baad, paanch din — bukhaar 100 ke upar ho tabhi lena. Raat ko Levocetirizine ek goli, paanch din; thodi neend aa sakti hai. Khaansi ke liye Ascoril LS das ml, din mein teen baar, paanch din. Telmisartan waise hi chalu rakhiye.
Khaane-peene mein kuch dhyaan rakhna hai?
Garam paani mein namak daal ke gargle, din mein 3–4 baar. Paani khoob piyo, aaram karo. Agar 48 ghante mein bukhaar nahi utra toh CBC aur dengue NS1 test karwa lena.
Teen din baad dikha dena. Saans phoole ya bukhaar 103 ke upar jaaye toh turant aana.
Theek hai doctor, dhanyavaad.
A normal Hinglish consultation. Nobody dictated, nobody typed. The phone on the desk heard it, and ScribeIn wrote this prescription — in English, on the clinic's letterhead.
What ScribeIn produces

What is said in the theatre
Chaliye, shuru karte hain. Sunita Deshmukh, 52 saal, female, IPD number DSH-2026-1012-088. Pre-op diagnosis symptomatic cholelithiasis. Procedure laparoscopic cholecystectomy. Surgeon main, assistant Dr. Neha Rane, anaesthesia Dr. Sameer Joshi, general.
Patient stable hai. BP 118 by 76, saturation 99, heart rate 72. Time-out done.
Supine position. Umbilical 10 mm port open technique se, pneumoperitoneum CO2 12. Epigastric 10 mm aur do 5 mm right subcostal ports under vision.
Grasper aur hook ready hai, sir.
Neha, fundus ko thoda cephalad retract karo. (looking at the screen) Findings: gallbladder distended hai, wall thick, fundus pe omental adhesions. Multiple stones palpable. CBD normal calibre, liver normal.
Calot's triangle dissect kiya, critical view of safety achieved. Cystic artery clipped — teen clips — aur divided. Cystic duct bhi teen clips, divided.
Clip applier, sir. Do clips bache hain, reload rakha hai.
Gallbladder liver bed se hook cautery se dissect kiya. Spillage nahi hua. Haemostasis confirmed. Specimen bag mein epigastric port se retrieve kiya. Drain nahi rakha.
Vitals steady, end-tidal CO2 theek hai. Reversal ready rakh raha hoon.
Ports under vision nikaale. Umbilical fascia Vicryl 1 se, skin Monocryl 3-0. Blood loss roughly 20 ml. Specimen gallbladder histopath ke liye.
Post-op: NBM 4 ghante, phir sips. IV fluids, Pantoprazole 40 IV once, Paracetamol 1 gram IV teen baar, Ondansetron SOS. Shaam ko mobilise. Kal subah discharge agar diet tolerate kare. Saat din baad wound check.
Extubated. Recovery mein shift kar rahe hain.
Fifty-five minutes of surgery, three people talking, the surgeon's hands never left the instruments. The collar mic heard it all; ScribeIn kept what matters clinically, dropped the chatter, and had this operative note ready for review before the patient reached recovery.
What ScribeIn produces
Pre-operative Diagnosis
Symptomatic cholelithiasis.
Post-operative Diagnosis
Chronic calculous cholecystitis with multiple gallstones.
Procedure Performed
Laparoscopic cholecystectomy, four-port technique.
Anaesthesia
General anaesthesia with endotracheal intubation. Pre-induction BP 118/76 mmHg, SpO₂ 99%, HR 72/min. Surgical time-out completed.
Operative Findings
- Gallbladder distended with a thickened wall; omental adhesions at the fundus
- Multiple stones palpable within the gallbladder
- Common bile duct of normal calibre; liver normal
- No bile or stone spillage
Technique
- Supine position. 10 mm umbilical port by open technique; pneumoperitoneum with CO₂ at 12 mmHg
- 10 mm epigastric and two 5 mm right subcostal ports placed under vision
- Fundus retracted cephalad; Calot's triangle dissected to the critical view of safety
- Cystic artery clipped (3 clips) and divided; cystic duct clipped (3 clips) and divided
- Gallbladder dissected off the liver bed with hook cautery; haemostasis confirmed
- Specimen retrieved in a bag through the epigastric port; no drain placed
- Ports removed under vision; umbilical fascia closed with Vicryl 1, skin with Monocryl 3-0
Estimated Blood Loss
Approximately 20 ml.
Post-operative Plan
- Nil by mouth for 4 hours, then sips; IV fluids until oral intake is adequate
- Inj. Pantoprazole 40 mg IV once daily · Inj. Paracetamol 1 g IV three times a day · Inj. Ondansetron 4 mg IV SOS
- Mobilise the same evening
- Specimen (gallbladder) sent for histopathology
- Discharge next morning if tolerating diet; wound check and review on day 7
Inside the app
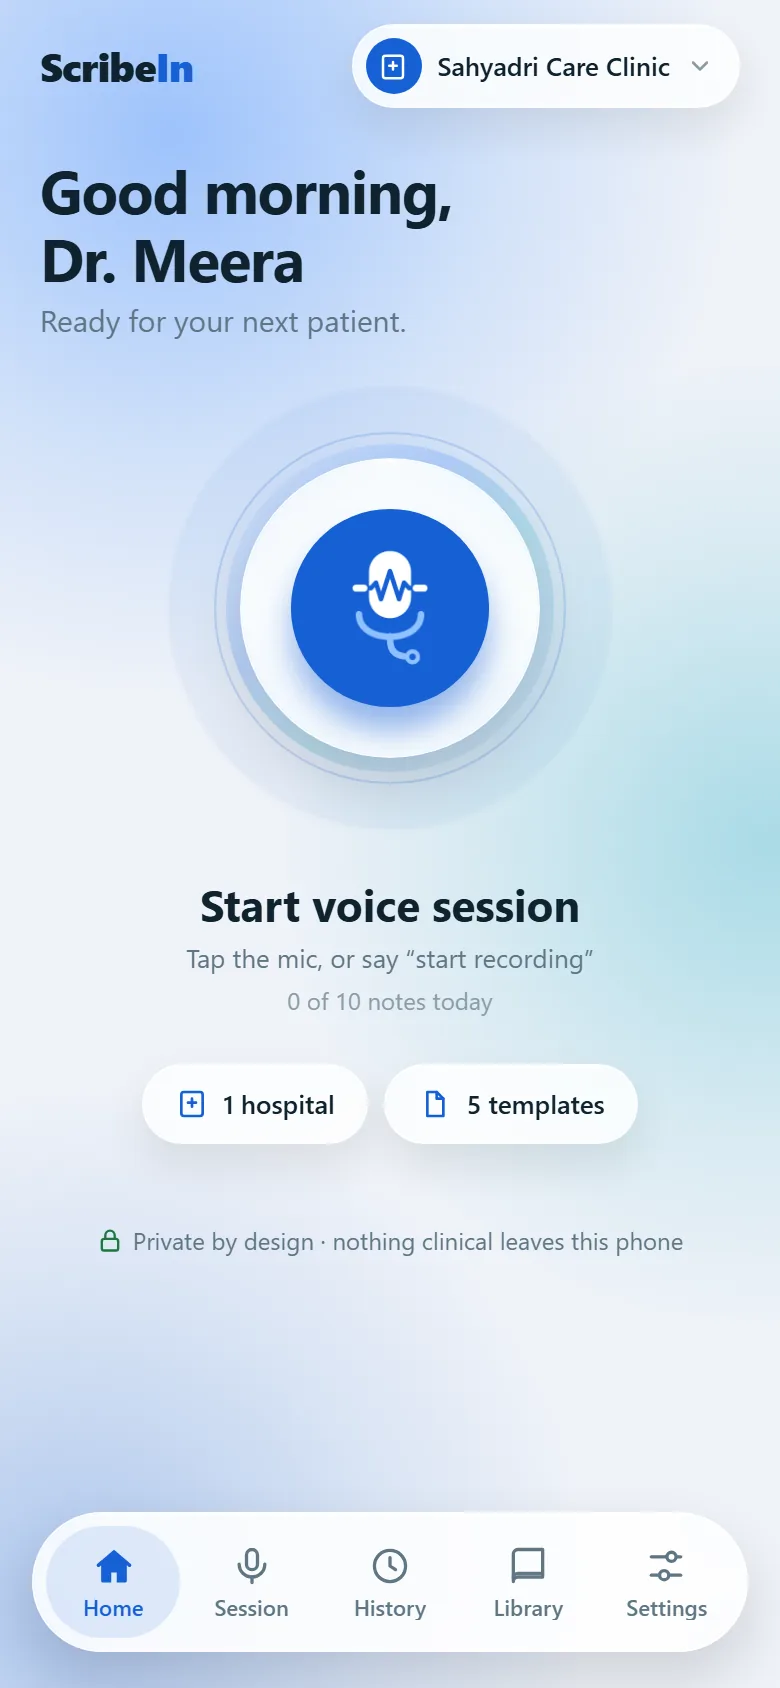
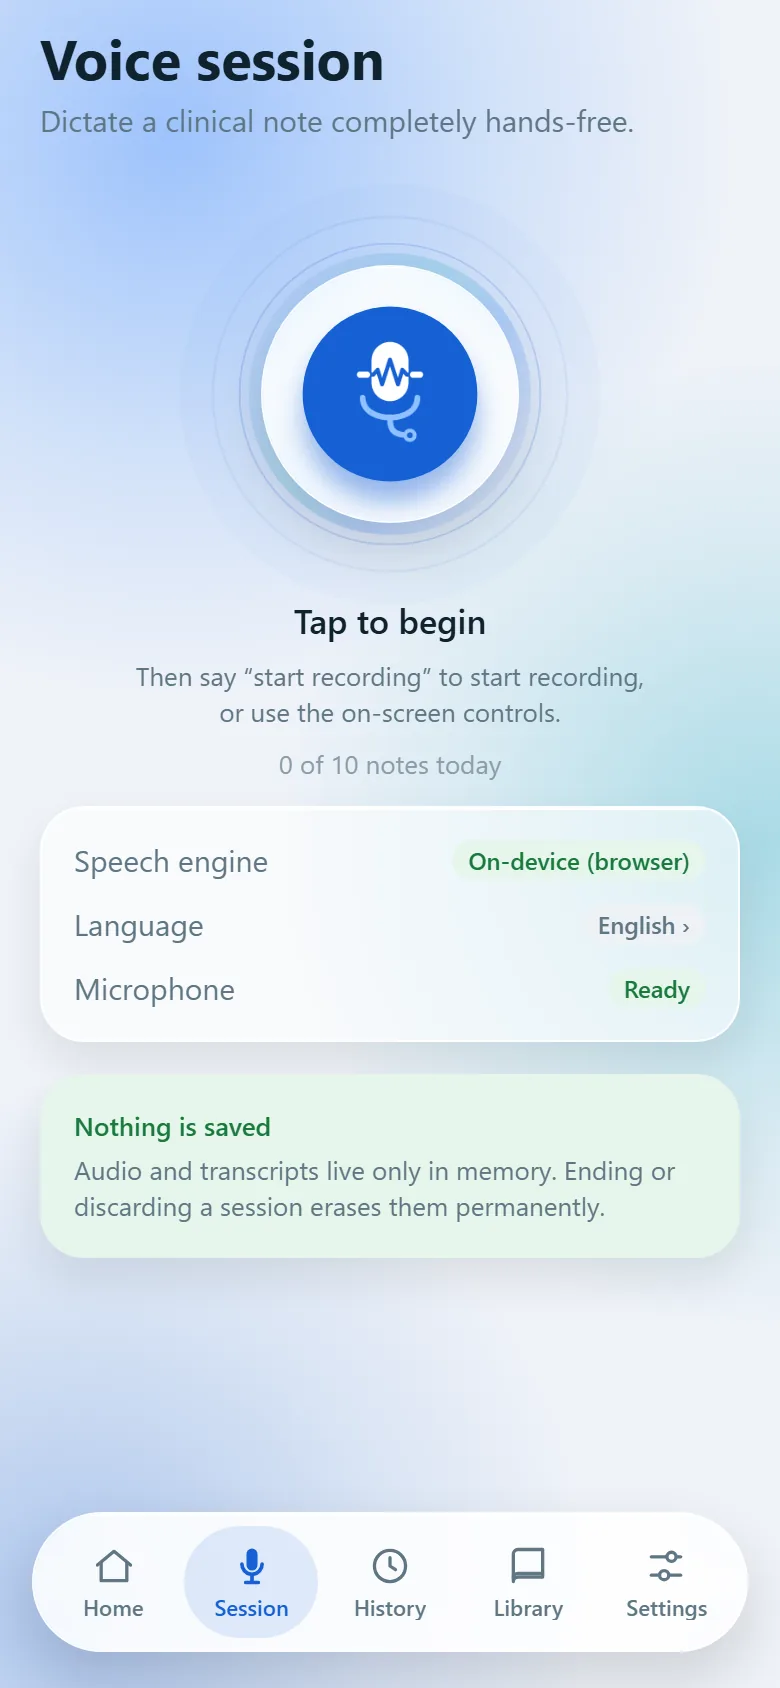
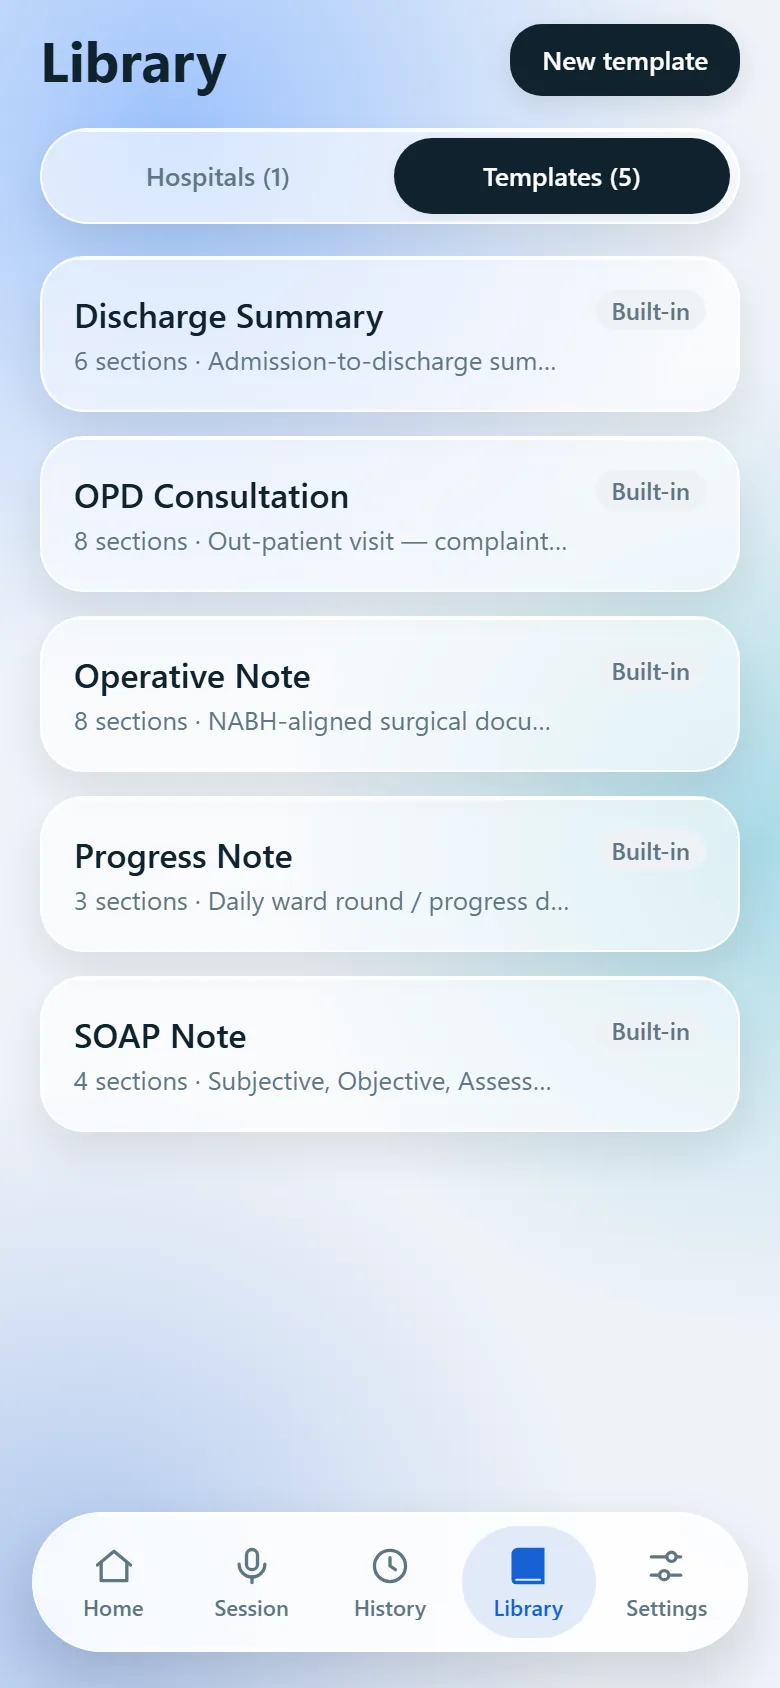
Screens from the current build. The doctor shown is fictional.
Finish the paperwork while the patient is still in the room.
Request early access and we will set ScribeIn up on your phone.